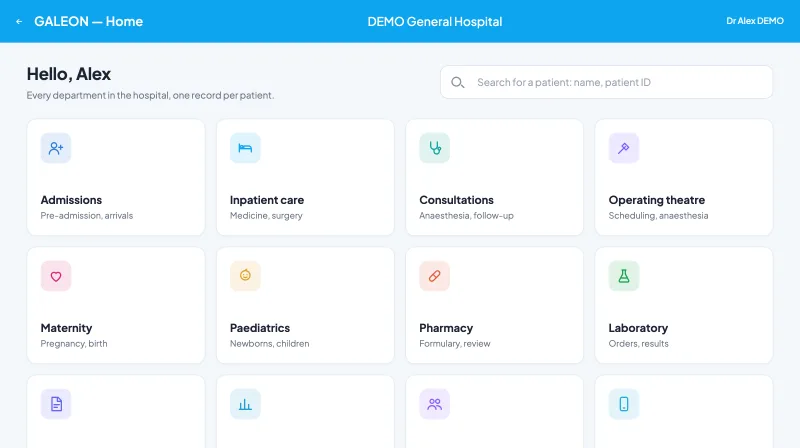
 See Galeon for real

Health Data Interoperability : Why It Is the Top Priority for French Hospitals in 2026
By 2026, data interoperability has evolved from a technical ambition into the strategic backbone of the French healthcare system.

The Essentials in 30 Seconds
| Question | Short Answer | What You Need to Remember |
|---|---|---|
| What is health data interoperability? | Unified exchange between hospital systems | Without it, hospitals are silos. Data must follow the patient to avoid decisions based on incomplete information. |
| Why is it the top priority in 2026? | Regulatory deadlines & safety costs | 2026 is the tipping point: technical debt becomes unsolvable for those who don't act on Ségur requirements now. |
| Ségur du Numérique requirements? | Mandatory FHIR adoption | All vendors funded under the programme must use FHIR. Non-compliant hospitals risk losing access to public funding. |
| Risks of fragmented HIS? | Medical errors & cyber-vulnerability | 1 in 5 emergency admissions involves care delays due to inaccessible data. Redundant tests and manual re-entry increase risks. |
| Where should a CIO start? | Audit of exchange flows | Identifying what circulates (and what doesn't) is the essential prerequisite for any successful FHIR migration. |
| Cost of inaction? | Doubling technical debt | Technical debt doubles every 4 years. Waiting costs more than acting due to lost public funding and increased cyber risk. |
Introduction
A patient admitted to emergency at 11pm. Their oncology history is in the EHR of a hospital 40 kilometres away. Their recent lab results are in a community software system incompatible with the hospital's infrastructure. Their anticoagulant treatment isn't recorded in the admission file. The on-call physician makes a decision with 60% of the information they need. This scenario isn't a hypothesis: according to DREES, it represents the daily reality for one third of emergency admissions in French hospitals in 2023.
Health data interoperability — the ability of systems to exchange medical information in a fluid, secure and intelligible way — is the technical undertaking that would prevent these situations. And in 2026, it is no longer merely a strategic ideal: it is a regulatory obligation, a clinical emergency and a competitiveness lever for French hospitals.
Galeon has made it the backbone of its architecture since 2016. Today deployed in 19 hospitals including two major university hospital centres (CHUs), with more than 3 million structured patient records and over 10,000 healthcare professional users, Galeon demonstrates that real interoperability — sovereign, secure, GDPR-compliant — is not only possible but operational at scale.
Why Has Health Data Interoperability Become Urgent in 2026?
Interoperability in healthcare is not a new topic. Hospital CIOs have been discussing it since the early 2000s. What changed in 2026 is the convergence of three simultaneous pressures that make inaction impossible: regulatory pressure, clinical pressure and technological pressure.
What Regulatory Pressure Are Hospitals Facing in 2026?
The Ségur du Numérique en Santé programme, led by the French Digital Health Agency (ANS), has required FHIR standard adoption by all health software vendors funded under the scheme since 2021. By 2026, successive Ségur waves have covered virtually the entire portfolio of hospital applications: EHR, laboratory, imaging, pharmacy and secure messaging.
Hospitals that have not updated their solutions to comply with ANS interoperability standards now face a dual penalty: loss of eligibility for public funding and progressive non-compliance with the European regulatory framework. The European Health Data Space (EHDS), whose regulation was adopted by the European Parliament in 2024, further reinforces this trajectory with a 2027–2028 horizon.
FHIR interoperability is no longer optional for French hospitals — it is a condition of access to public funding.
What Is the Real Clinical Impact of a Fragmented HIS?
The fragmentation of hospital information systems has a direct, measurable and documented clinical cost. The average French hospital HIS is composed of 50 to 200 distinct applications (ANS, 2023), a significant proportion of which do not communicate natively with one another.
The consequences include:
- Clinicians spend an average of 45 minutes per shift searching for information scattered across multiple systems (HCSP, 2022)
- Medical errors linked to missing or poorly transmitted information account for 10 to 15% of preventable adverse events in hospitals (HAS, 2023)
- Redundant examinations caused by inaccessible prior results represent an estimated cost of €4.5 billion annually in France (Cour des comptes, 2022)
A non-interoperable HIS is not merely inefficient. It is clinically dangerous.
Why Is the Window for Action Closing in 2026?
The technical debt of hospital information systems accumulates at a rate that outpaces teams' capacity to catch up. Every year without migrating to interoperable architectures adds another layer of bespoke connectors, conversion scripts and fragile middleware to the existing foundation.
Hospitals that begin their interoperability project in 2026 can still benefit from Ségur funding, a mature market offering and active ANS support. Those that wait until 2027 or 2028 will face exponentially higher migration costs, with no equivalent public support.
What Is Health Data Interoperability, Exactly?
Health data interoperability refers to the ability of heterogeneous IT systems to exchange medical data, interpret it correctly and reuse it without loss of information or meaning. It breaks down into three levels.
What Are the Three Levels of Health Interoperability?
The reference model distinguishes three progressive levels, each more demanding than the last:
Technical interoperability is the foundational level. It ensures that two systems can physically exchange data — that the connection exists, that file formats are compatible, that communication protocols are shared. This is the level at which most HL7 v2 integrations still in production in French hospitals operate.
Semantic interoperability is the critical level. It ensures that both systems interpret the data in the same way. A CIM-10 code for a diagnosis, a unit of measurement for a lab result, a drug name in INN rather than brand name. Without semantic interoperability, data arrives at its destination but may be misinterpreted.
Organisational interoperability is the rarest level. It ensures that the workflows of both institutions are compatible — that prescription, validation and sharing processes articulate correctly from one system to the other.
The majority of French hospitals have achieved partial technical interoperability. Very few have achieved complete semantic interoperability. Almost none have achieved organisational interoperability.
Why Is the FHIR Standard the Answer to Semantic Interoperability?
FHIR — Fast Healthcare Interoperability Resources — is the standard developed by HL7 International to address precisely the semantic interoperability challenge. Published in a stable version (R4) in 2019, it rests on a logic radically different from its predecessors.
FHIR treats every element of medical data — a patient, a medication, a clinical observation, a lab result — as a web resource, accessible via a standardised API. This means any FHIR-compatible system can query, receive and interpret these resources coherently, without bespoke development.
The concrete benefits for a hospital CIO include:
- Drastic reduction in integration costs: FHIR connectors are standardised and reusable across all compliant systems
- Real-time exchanges: data flows via synchronous API, without nightly batch processing
- Guaranteed semantic quality: FHIR mandates common terminologies (SNOMED CT, LOINC, ICD-11) for each data type
- Global adoption: FHIR is the standard mandated by the United States (ONC Cures Act, 2021), the European Union (EHDS, 2024) and the WHO
FHIR is the common language the global digital health ecosystem is adopting. Hospitals that don't speak it will gradually be left behind.
Interoperable Hospitals vs Fragmented Hospitals : The 2026 Comparison
| Access to the patient record | Partial, multi-interface, requires multiple logins | Unified, accessible from a single entry point via FHIR API |
| Information retrieval time | Average 45 min per shift (HCSP, 2022) | Reduced by 60 to 80% across Galeon pilot hospitals |
| Data sovereignty | Theoretical — data migrates to third-parties | Technical guarantee — data stays on hospital servers |
| Redundant examinations | Frequent (€4.5bn/year waste in France) | Strongly reduced through real-time access to prior results |
| Cybersecurity | Multiple failure points, unaudited integrations | Decentralised architecture & total flow traceability |
| Ségur funding | At risk if non-compliant with ANS standards | Secured through native compliance with FHIR standards |
| HIS scalability | Limited by technical debt & bespoke connectors | Modular, inherently extensible via standardised APIs |
What Are the Real Limits and Challenges of Hospital Interoperability?
Positioning interoperability as a priority is legitimate. Claiming its implementation is straightforward would be dishonest. Here are the real obstacles every hospital decision-maker must anticipate.
The coexistence of HL7 v2 and FHIR creates a complex transition period. Most systems in production in French hospitals still operate on HL7 v2. Migration to FHIR is inevitable, but it entails a period of coexistence between the two standards, with the hybrid interface maintenance costs that implies. There is no "smooth" migration that does not require dedicated human and financial resources.
Upstream data quality determines everything downstream. A performance standard as robust as FHIR cannot do anything with poorly entered, incomplete or heterogeneous data. Structuring data at the source — at the moment the clinician produces it — is a non-negotiable prerequisite. This is one of the most underestimated challenges in hospital digital transformation projects.
Resistance to change is often the first obstacle. Interoperability projects rarely fail for purely technical reasons. They fail because clinical teams were not involved from the outset, because the concrete benefits were not clearly explained, or because change management was treated as a residual budget item rather than a strategic investment.
Opening APIs increases the cyber attack surface. The more interoperable a HIS is, the more potential entry points it exposes to malicious actors. Interoperability must be accompanied by a strengthened security policy: strong authentication, end-to-end encryption, real-time flow monitoring. ANSSI recommends integrating security from the design phase, not as an afterthought.
Inter-institutional governance is a political challenge as much as a technical one. Getting multiple institutions to collaborate on a shared data network requires formal agreements on responsibilities, access rights, data use conditions and conflict resolution mechanisms. This level of governance takes time and requires high-level leadership — including CEOs, CIOs and medical directors.
FAQ — Questions CIOs Ask About Health Data Interoperability in 2026
Does achieving FHIR interoperability require replacing the entire HIS? No. FHIR is designed to integrate progressively with existing systems via adaptation layers called FHIR middleware. It is entirely possible to maintain HL7 v2 systems in production while deploying FHIR APIs for new exchange flows. Migration is carried out by successive functional domains — laboratory, prescriptions, clinical reports — without global operational disruption. A data flow mapping audit is the recommended starting point.
Does the Ségur du Numérique directly require hospitals to adopt FHIR? The Ségur requires compliance with ANS interoperability standards from health software vendors funded under the programme. For hospitals, this means that the solutions they deploy or renew must be compliant to be eligible for financial support. In practice, any renewal of an EHR, laboratory or imaging system will be subject to this FHIR compliance requirement.
In this model, data remains physically on each hospital's servers. AI algorithms travel across the network, train locally on each dataset, and return only the model's statistical parameters — never raw data.
What are realistic timelines for an interoperability project in a mid-sized hospital? A FHIR interoperability project for a mid-sized hospital (300 to 600 beds) typically spans 18 to 36 months, depending on the complexity of the existing HIS and the number of systems to connect. Typical phases are: audit and mapping (3–4 months), solution selection and contracting (3–6 months), deployment by functional domains (12–24 months), validation and scaling (6–12 months).
What funding is available for an interoperability project in 2026? Ségur du Numérique en Santé funding remains the main source of public support for interoperability projects. It covers investments related to bringing EHR, laboratory, imaging and secure messaging software into compliance. Amounts vary by wave and institution type. ANS regularly publishes eligibility standards on its official website. Regional funding and FMIS credits (Fonds de Modernisation des Investissements en Santé) complement this scheme.
In Summary: What You Need to Know About Health Data Interoperability in 2026
The FHIR standard establishes a common language the entire global digital health ecosystem is adopting. The Galeon model — 19 partner hospitals, more than 3 million structured records, 10,000 healthcare professional users — demonstrates that real interoperability, sovereign and capable of powering cutting-edge medical AI, is operational today, not in ten years. Hospitals that launch this initiative in 2026 are building the infrastructure that will make all of tomorrow's medicine possible.
Discover our interoperable DPI
Book a demoSources
Cour des comptes, Public Hospitals Facing Their Challenges - Report on Public Health Finances, 2022.
Related reading
They trust us
19 hospitals running Galeon in France.
















Join the pioneers of care.

 2 sales reps available from tomorrow
Your IT, your interfaces, your timeline. Pick a slot: Valérie or Yohan will call you back.
- HDS certified
- ISO 27001
- GDPR compliant
- LAP certified (HAS)